
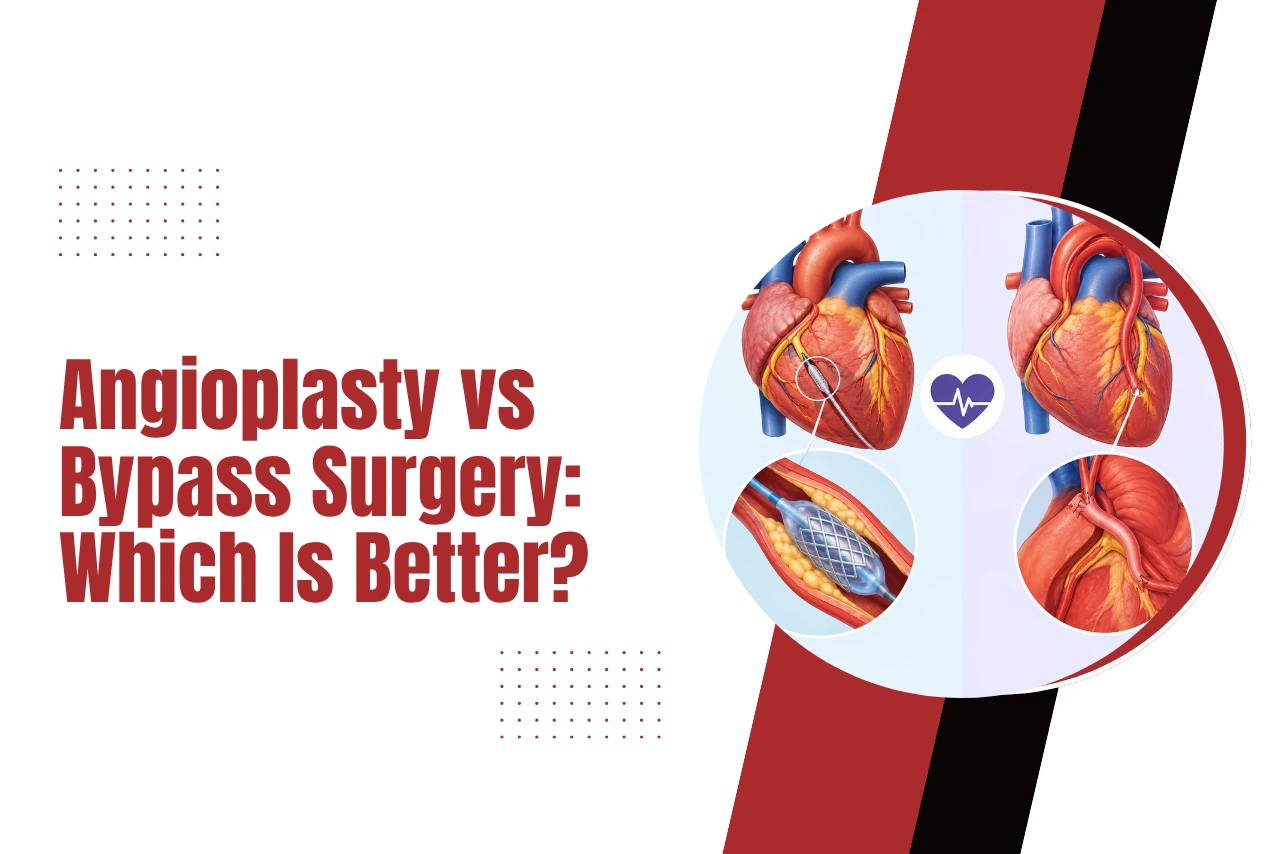
Patients ask this question a lot, and there’s genuinely no single answer waiting for them. What decides it isn’t which procedure sounds less invasive. It’s the angiogram. How many arteries are blocked, where exactly those blockages sit, how tangled up the anatomy is, plus whatever else is going on with a patient’s overall health. That’s the actual starting point for anyone trying to work out the difference between bypass and angioplasty, not a gut feeling about which surgery sounds scarier.
According to Dr. Kiran Narang, an interventional cardiologist, the choice of treatment for blocked coronary arteries depends on angiogram findings, including the number, location and severity of blockages. These factors, along with the patient’s overall health and other clinical considerations, help determine whether medication, angioplasty or bypass surgery may be appropriate.
Which Option Has Better Long-Term Outcomes?
This question sits underneath almost every angioplasty vs bypass conversation, and the honest answer depends on the individual case.
This question sits underneath almost every angioplasty vs bypass conversation, and the honest answer depends on the individual case.
For single or double vessel disease, angioplasty often holds up just as well as bypass, and the recovery is much shorter. Things change once multivessel disease or left main involvement enters the picture. Larger comparative studies suggest bypass surgery may edge ahead on long-term survival when the disease is more extensive, particularly in older patients.
Diabetes can tip the scale too. Patients with diabetes and several blocked vessels often do better long-term with bypass than with angioplasty. There’s also the question of what happens years down the line. Angioplasty may need to be repeated at some point, while bypass grafts, once in place, often last longer without a redo.
If you’ve already had angioplasty or are weighing it right now, our piece on angioplasty recovery walks through what the weeks afterward look like.
For information about angioplasty and bypass surgery options, you can contact the clinic at +91 99674 82300 .
What’s the Difference Between Angioplasty and Bypass Surgery?
Both procedures address the same underlying problem, a blocked or narrowed artery, but doctors address it in very different ways.
Angioplasty:
A catheter makes its way through a blood vessel until it reaches the blockage. Once there, a balloon widens the narrowed section, and a stent is usually placed to help keep the artery open. No open-heart surgery needed for any of this.
Bypass surgery (CABG):
This one bypasses the blockage entirely. Surgeons build a new route for blood flow using a graft, often taken from a blood vessel in the leg or chest. It involves open-heart surgery.
Combined heart risk:
This one bypasses the blockage entirely. Surgeons build a new route for blood flow using a graft, often taken from a blood vessel in the leg or chest. It involves open-heart surgery.
Recovery time:
Someone who’s had angioplasty might be home the next day, sometimes even the same one. Bypass surgery means roughly a week in the hospital, and recovery stretches on for weeks after discharge.
Best suited for
A single blockage, or a limited one, usually responds well to angioplasty. Once several vessels are involved, especially when the left main artery is affected, bypass surgery is often considered a more suitable option.
If angioplasty looks like the right fit after your angiogram, our Angioplasty page explains the procedure in more detail.
What Determines the Right Choice Between Angioplasty and Bypass Surgery?
Doctors weigh several factors together, not one test result. Each of them can shift the recommendation.
- The number of blocked arteries matters. One or two narrowed vessels are often suited to angioplasty. Three or more may point towards bypass surgery.
- Location counts as much as number. The left main artery supplies a large part of the heart, so a blockage there is assessed very carefully.
- The shape of the blockage plays a part. Long, branching or heavily hardened blockages can be harder to hold open with a stent.
- Other health conditions can tip the balance. Diabetes, reduced pumping strength of the heart or kidney problems may favour one approach, and age and fitness for surgery are considered too.
- The situation itself is reviewed. A heart attack may need quick angioplasty, while a planned decision leaves time for a joint review by the cardiologist and cardiac surgeon.
Key Takeaways:
- There’s no single better option. The choice depends on the angiogram and the patient’s overall health.
- Angioplasty is the less invasive route. A catheter, a balloon and usually a stent are used, with no open-heart surgery.
- Bypass surgery reroutes blood around the blockage. It’s often considered when several vessels or the left main artery are involved.
- Long-term results can differ. Diabetes and the number of blocked vessels may influence which option holds up better.
- Repeat procedures vary by approach. Angioplasty may need repeating over time, while bypass grafts often last longer.
FAQ’s
How do I know if I need bypass surgery instead of angioplasty?
It really comes down to what the angiogram shows, how many vessels are blocked, and whether the left main artery’s involved. A cardiologist won’t recommend either option without seeing that full picture first.
Is angioplasty less risky than bypass surgery?
Mostly, yes, it’s the less invasive route with a quicker recovery attached. That said, lower risk on the table doesn’t automatically translate to the better outcome down the road, especially once multiple vessels are blocked.
Can angioplasty be done again if a blockage returns?
Usually, yes. A repeat angioplasty isn’t unusual and tends to go smoothly. Though if restenosis keeps coming back, that’s often the point where bypass surgery gets raised as the next step.
How long do bypass grafts typically last?
Grafts using the internal mammary artery often outlast a decade, sometimes by a wide margin. Vein grafts don’t tend to hold up as long, somewhere around 8 to 10 years is typical before complications start creeping in.
References
- Weintraub WS, et al. Comparative Effectiveness of Revascularization Strategies. New England Journal of Medicine, PubMed Central. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4671393/
- Percutaneous Coronary Intervention. StatPearls, NCBI Bookshelf. https://www.ncbi.nlm.nih.gov/books/NBK556123/
Disclaimer: This content is for educational purposes only and should not be considered a substitute for professional medical advice, diagnosis, or treatment.